
Clinical guide
Heroin Addiction: Signs, Health Risks, Overdose, and Treatment
Heroin is an illegal opioid that can cause opioid use disorder and fatal overdose. Learn the signs, health risks, withdrawal symptoms, and treatments.
By Paul James Roeser·Reviewed by Dr. Michael Olla, MD·Last reviewed August 22, 2026·9 min read
Published ·Updated
Heroin is an illegal, rapidly acting opioid that can cause opioid use disorder, respiratory depression, and fatal overdose. It is made from morphine and is sold as white or brown powder or as a dark, sticky substance commonly called black tar heroin. Illicit products have unpredictable strength and may contain fentanyl or other substances.
Heroin addiction is clinically assessed as opioid use disorder. The disorder involves impaired control over opioid use, continued use despite harm, and changes in daily functioning; tolerance or physical dependence alone does not establish the diagnosis.
What is heroin?
Heroin is a Schedule I opioid made from morphine. The Drug Enforcement Administration classifies heroin as having no currently accepted medical use in the United States and a high potential for misuse. The National Institute on Drug Abuse describes heroin as white or brown powder or black tar, but appearance cannot reveal purity, potency, or contaminants.
Clinical assessment considers the substance, route, frequency, and consequences rather than relying on appearance. People may inject, smoke, or snort heroin. Every route can cause intoxication, dependence, addiction, and overdose; avoiding injection may reduce needle-related infection risk but does not make heroin use safe.

Clinical perspective
Heroin's withdrawal timeline is brutal but predictable, which is actually useful — day three can be described in advance, and knowing that helps people get through it instead of being ambushed by it. Predictability doesn't make it easy. It makes it survivable with the right support.

What are common heroin street names?
Common heroin street names include dope, smack, horse, H, junk, brown sugar, and black tar. Terms such as China White, white powder, or purple heroin are especially unreliable because they may refer to heroin, fentanyl, another synthetic opioid, or a mixture.
Street language describes a seller's claim or a product's appearance rather than a verified chemical identity. Color, texture, stamp, and price cannot show whether a sample contains fentanyl, xylazine, or another adulterant.

How does heroin affect the brain and body?
Heroin activates opioid receptors and suppresses central nervous system activity. Its immediate clinical effects can include euphoria, pain relief, warmth, drowsiness, confusion, constricted pupils, nausea, and constipation. Its most dangerous effect is respiratory depression, which means breathing becomes too slow or shallow to supply enough oxygen.
Repeated exposure can produce tolerance, so a person needs more heroin to reach a previous effect, and physical dependence, so stopping produces withdrawal. These adaptations can occur with opioid use, while addiction adds compulsive use and continued use despite consequences. Heroin belongs to the broader opioid drug class, which also includes prescription and synthetic opioids.
Which Routes of Administration Carry Risk?
Heroin is injected, smoked, or snorted, and each route delivers an unregulated opioid dose with overdose potential. Injection produces the fastest onset and adds blood-borne infection, vascular injury, abscess, and endocarditis risk. Smoking and snorting avoid needle exposure but still cause respiratory depression, dependence, opioid use disorder, and overdose.
Route can change onset and intensity without making the supply predictable. Fentanyl contamination also means a person may receive a much more potent opioid than expected regardless of how the product is consumed.

What are the signs of heroin addiction?
Heroin addiction causes impaired control, craving, risky use, and continued use despite harm. A person may use more than intended, spend substantial time obtaining or recovering from heroin, make unsuccessful attempts to stop, or withdraw from work, school, relationships, and usual activities.
Physical and behavioral signs can include sedation, constricted pupils, changing sleep, constipation, neglected responsibilities, secretive use, financial problems, injection marks, and recurring withdrawal. No single sign proves opioid use disorder, so diagnosis requires a clinical assessment of the whole pattern.
What health problems can heroin use cause?
Heroin use can damage respiratory, cardiovascular, gastrointestinal, neurological, and infectious-disease health. Clinical effects can include slowed breathing, constipation, nausea, impaired judgment, and increased sensitivity to pain after long-term use.
Injection adds risks from contaminated equipment and unsterile products, including skin and soft-tissue infection, collapsed veins, endocarditis, hepatitis B, hepatitis C, and HIV. Mixing heroin with alcohol, benzodiazepines, or other sedatives compounds respiratory depression and raises overdose risk.
What Are the Immediate Opioid Effects?
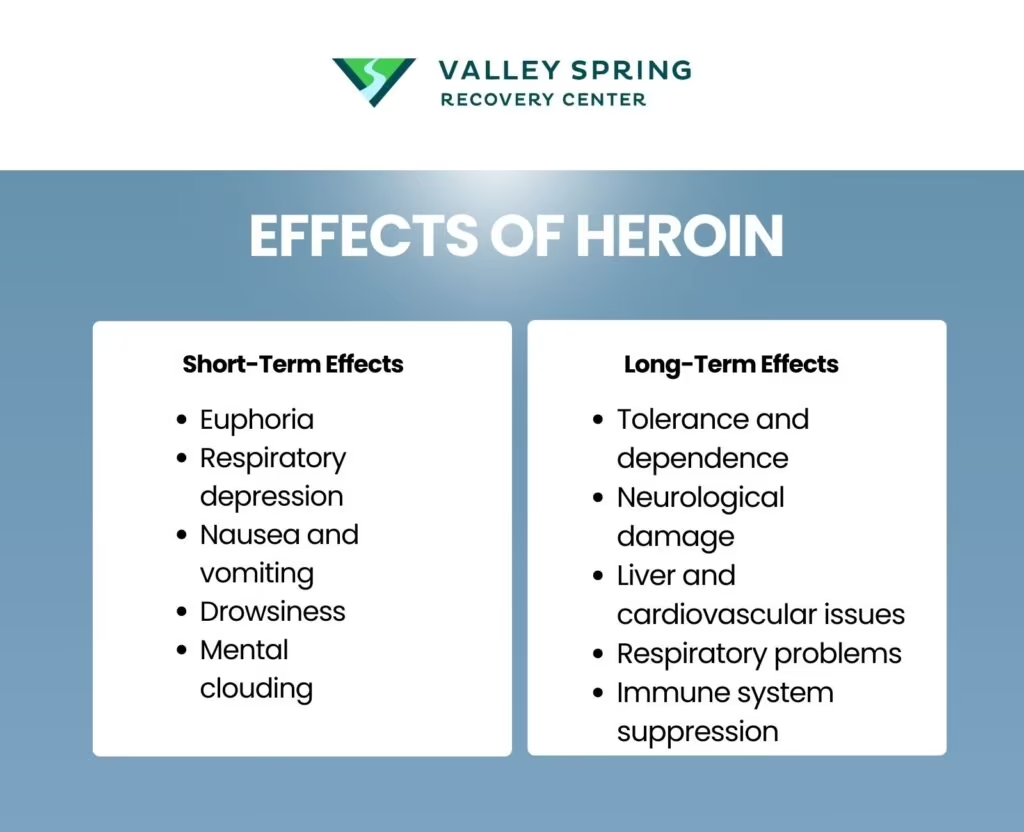
Short-term heroin effects include a rapid rush or euphoria, warmth, heavy limbs, dry mouth, nausea, itching, constricted pupils, drowsiness, slowed thinking, constipation, and respiratory depression. The subjective high commonly gives way to alternating wakefulness and sedation. Vomiting while consciousness is impaired adds aspiration risk.
What Health Effects Develop With Repeated Use?
Long-term heroin exposure can produce tolerance, physical dependence, opioid use disorder, chronic constipation, sleep disruption, hormonal changes, mood symptoms, and recurring overdose risk. Injection can add scarring, damaged veins, recurrent abscesses, endocarditis, and viral hepatitis or HIV exposure. An adulterated supply introduces additional injuries that cannot be predicted from heroin alone.
Which Symptoms Occur During Opioid Withdrawal?
Heroin withdrawal causes a cluster of physical distress, craving, and sleep disruption after opioid use is reduced or stopped. NIDA lists muscle and bone pain, cold flashes, cramps, diarrhea, restlessness, vomiting, and involuntary leg movements among common symptoms.
Withdrawal severity depends on the pattern of use, other substances, health conditions, and prior treatment. Medical assessment can address dehydration, pregnancy, co-occurring illness, and medication options. Detoxification by itself does not treat the underlying opioid use disorder and can leave a person vulnerable to overdose if opioid use resumes after tolerance falls.
What are the signs of a heroin overdose?
A heroin overdose makes a person difficult to wake and slows, interrupts, or stops breathing. Other signs can include pinpoint pupils, blue or gray lips or nails, clammy skin, choking or gurgling sounds, and a limp body. Emergency care should begin when overdose is suspected because waiting for every sign can delay lifesaving treatment.
Call 911, give naloxone for a suspected opioid overdose, support breathing or perform CPR if trained, place the person on their side when appropriate, and stay until emergency responders arrive. A new naloxone dose may be needed if normal breathing does not return or respiratory depression returns.
How many overdose deaths involve heroin?
CDC final mortality data recorded 2,743 U.S. drug overdose deaths involving heroin in 2024. CDC reported a corresponding crude rate of 0.8 deaths per 100,000 people. These records identify heroin involvement rather than heroin acting alone, because the same death can include fentanyl, cocaine, alcohol, benzodiazepines, or other substances.
The heroin count was far below the 47,735 deaths involving synthetic opioids other than methadone in the same CDC dataset. The categories should not be added together, and the lower heroin count does not make any illicit opioid supply predictable or safe. Prevention programs should interpret both categories without assuming that they describe separate groups of deaths.

How long does a heroin high last?
Heroin's noticeable effects generally last several hours, while onset depends strongly on route. Injection reaches the brain within seconds, and smoking or snorting has a slower onset. The brief initial rush can be followed by hours of sedation, impaired judgment, and slowed breathing, so the end of euphoria does not mark the end of overdose risk.
Duration varies with dose, tolerance, other drugs, and whether the supply contains fentanyl. A person who remains difficult to wake or breathes slowly after the expected high needs an overdose response, not observation until the drug “wears off.”
How long does heroin remain detectable?
Heroin itself clears quickly, while its metabolites remain detectable longer and specimen type determines the testing window. Urine generally reflects exposure over days, oral fluid and blood emphasize more recent use, and hair can reflect a longer history. Laboratory cutoffs, dose, repeated exposure, metabolism, and collection timing prevent one exact timeline from applying to every test.
A positive toxicology result establishes exposure above a cutoff; it does not establish impairment, dose, or opioid use disorder severity. Urine, blood, oral-fluid, and hair results therefore require interpretation against the specimen, cutoff, collection time, and clinical question.
How is heroin addiction treated?
Heroin addiction treatment combines medication for opioid use disorder with individualized clinical and recovery support. The FDA-approved medications are methadone, buprenorphine, and naltrexone. CDC guidance states that medication treatment is associated with lower overdose and overall mortality risk and that detoxification alone is not recommended for opioid use disorder.
Assessment determines withdrawal needs, overdose history, other substance use, physical health, mental health, housing, and the appropriate level of care. Counseling, cognitive behavioral therapy, peer support, family services, case management, and harm-reduction planning can support medication and long-term recovery.
A structured heroin addiction treatment program in New Jersey can coordinate medication, therapy, relapse prevention, and care for co-occurring conditions across outpatient levels of care.
How can a person reduce relapse and overdose risk?
A recovery plan reduces relapse and overdose risk by combining continuing treatment, naloxone access, practical support, and rapid response to warning signs. Risk often rises after detoxification, hospitalization, incarceration, or any other period without opioid use because tolerance can decline.
Continuing medication when prescribed, attending follow-up care, treating pain and mental health symptoms, avoiding sedative combinations, carrying naloxone, and involving trusted support can strengthen recovery. A return to use signals that the treatment plan needs reassessment; it does not erase prior progress.
Which Adulterants and Drug Combinations Raise Risk?
Heroin may be mixed with fentanyl, xylazine, quinine, sugars, starches, or other powders, while people may separately combine it with cocaine, alcohol, or benzodiazepines. The contents and concentration of an illicit sample cannot be confirmed by color, texture, taste, or street name.
A heroin-and-cocaine combination is often called a speedball. Cocaine does not cancel opioid respiratory depression, and the stimulant can add arrhythmia, overheating, seizure, and cardiovascular stress. Alcohol and benzodiazepines push breathing in the same dangerous direction as heroin. Naloxone should still be given when an opioid may be involved, even when the mixture is uncertain.
How Can Families Respond to Opioid Use and Overdose Risk?
Families can support treatment by responding to overdose risk, discussing observed behavior without shame, and setting clear boundaries. Household members should know where naloxone is stored, how to use it, and when to call 911.
A calm conversation should describe specific changes rather than assign a diagnosis. Families can offer help arranging an assessment or transportation while declining to provide money, conceal consequences, or manage severe withdrawal without clinical guidance.

Frequently Asked Questions
Is heroin a depressant or a stimulant?
Heroin is a central nervous system depressant. It activates mu-opioid receptors and slows breathing and alertness rather than increasing central nervous system activity like cocaine or methamphetamine.
Is black tar heroin safer than white powder heroin?
No. Appearance does not establish dose, purity, or contaminants. Black tar and powder heroin both cause opioid use disorder and overdose, and either may contain fentanyl or other substances.
Can heroin withdrawal cause death?
Opioid withdrawal is usually not fatal by itself, but persistent vomiting and diarrhea can cause dangerous dehydration and electrolyte disturbance. Pregnancy, serious illness, sedative withdrawal, and rapid return to opioid use after tolerance falls add further risk and require clinical assessment.
Sources & References6ShowHide
- National Institute on Drug Abuse. Heroin — Federal overview of heroin, its forms, health effects, withdrawal, overdose risk, and treatment.
- National Institute on Drug Abuse. Drugs A to Z: Heroin — Current heroin classification, effects, health risks, withdrawal symptoms, and approved treatments.
- U.S. Drug Enforcement Administration. Heroin Drug Fact Sheet — Heroin appearance, routes of use, Schedule I status, physical effects, and overdose signs.
- CDC National Center for Health Statistics. FastStats: Drug Overdoses — Final 2024 national overdose mortality counts, including deaths involving heroin.
- CDC. Opioid Use Disorder: Treating — Evidence-based treatment guidance for medications, behavioral services, naloxone, and the limits of detoxification alone.
- SAMHSA. TIP 63: Medications for Opioid Use Disorder — Federal guidance on assessment, methadone, buprenorphine, naltrexone, and recovery support for opioid use disorder.