
Addiction guide
Addiction: Definition, Types, Causes and Treatment
Addiction is a chronic, relapsing brain disorder of compulsive substance use or behavior. Learn its types, causes, symptoms, diagnosis, and treatment in NJ.
By Paul James Roeser·Reviewed by Noelle Mathew, LCSW, LCADC, CASAC-M·Last reviewed August 26, 2026·16 min read
Published ·Updated
Addiction is a chronic, relapsing disorder defined by compulsive substance seeking and use, or compulsive engagement in a behavior, that continues despite harmful consequences. The National Institute on Drug Abuse (NIDA) classifies addiction as a brain disorder because it produces functional changes in the brain circuits that govern reward, stress, and self-control. The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) diagnoses the substance form of addiction as substance use disorder (SUD), measured against 11 criteria and graded mild, moderate, or severe.
According to the Substance Abuse and Mental Health Services Administration's (SAMHSA) 2024 National Survey on Drug Use and Health (NSDUH), 48.4 million Americans aged 12 or older — 16.8 percent of the population — had a substance use disorder in the past year. Alcohol use disorder affected 27.9 million people, drug use disorder affected 28.2 million people, and opioid use disorder affected 4.8 million people.
U.S. overdose deaths are falling. The United States recorded 79,384 drug overdose deaths in 2024, and the age-adjusted overdose death rate fell 26.2 percent from 2023 — the largest one-year drop of the 2014-2024 period, according to the CDC's National Center for Health Statistics. New Jersey recorded more than 2,800 overdose deaths in 2023, an 11 percent decline from 2022, and preliminary 2024 data shows a further decrease, according to the New Jersey Department of Health.
Addiction is treatable, and treatment remains underused: among Americans classified as needing substance use treatment in 2024, 19.3 percent — 10.2 million people — received it, per the 2024 NSDUH.
What Is Addiction?
Addiction is a chronic, relapsing disorder characterized by compulsive drug seeking and use despite adverse consequences, as the National Institute on Drug Abuse defines it in "Drugs, Brains, and Behavior: The Science of Addiction." NIDA considers addiction a brain disorder because it involves functional changes to brain circuits involved in reward, stress, and self-control.

The DSM-5 folded the older diagnoses of substance abuse and substance dependence into the single diagnosis of substance use disorder. A person meets the diagnosis by satisfying 2 or more of 11 criteria within a 12-month period, according to Jahan, Azmi R. and Burgess, Doug M.'s 2023 StatPearls review "Substance Use Disorder," published by the National Library of Medicine. Severity scales with the criterion count: 2 to 3 criteria is mild, 4 to 5 is moderate, and 6 or more is severe.
Every substance use disorder changes motivation, reward, stress, and self-control, while the specific drug determines the speed and pattern of those changes. Addiction changes the brain through interacting effects on dopamine signaling, neuroplasticity, stress circuits, and executive control.
How Does Addiction Change the Brain?
Addiction changes the brain by flooding the reward circuit with dopamine, then weakening the circuits that regulate stress and self-control, according to NIDA's "Drugs, Brains, and Behavior: The Science of Addiction." Brain imaging in that report shows people with a history of cocaine use disorder carry lower levels of the D2 dopamine receptor in the striatum than people who never used cocaine.
Repeated dopamine surges teach the brain to rank the substance above natural rewards, including food, social connection, and accomplishment. Addiction also alters the brain's self-control circuits, according to NIDA's report "Drug Misuse and Addiction" — which is why willpower alone fails as a treatment plan: the circuitry that governs decisions is itself changed.
The brain changes also separate addiction from the related but distinct state of physical dependence.
What Is the Difference Between Addiction and Dependence?
The difference between addiction and dependence is that addiction is compulsive use despite harmful consequences, while dependence is the body's physical adaptation to a substance, producing tolerance and withdrawal when use stops. A hospital patient on long-term opioid therapy develops dependence without addiction, and the DSM-5 omits the tolerance criterion for medications taken under physician supervision, per Jahan and Burgess's StatPearls review.
Physical dependence without addiction is managed through a physician-supervised taper. Addiction adds the behavioral pattern — craving, loss of control, and continued use despite consequences — and requires treatment of behavior as well as physiology.
What Are the Types of Addiction?
The 2 types of addiction are substance addiction, involving alcohol or drugs, and behavioral addiction, involving compulsive engagement in activities such as gambling. The DSM-5 formalized the second category by moving gambling disorder into its substance-related and addictive disorders chapter, according to Rash, Carla J. and Petry, Nancy M.'s 2016 article "Gambling Disorder in the DSM-5," published in Current Addiction Reports.
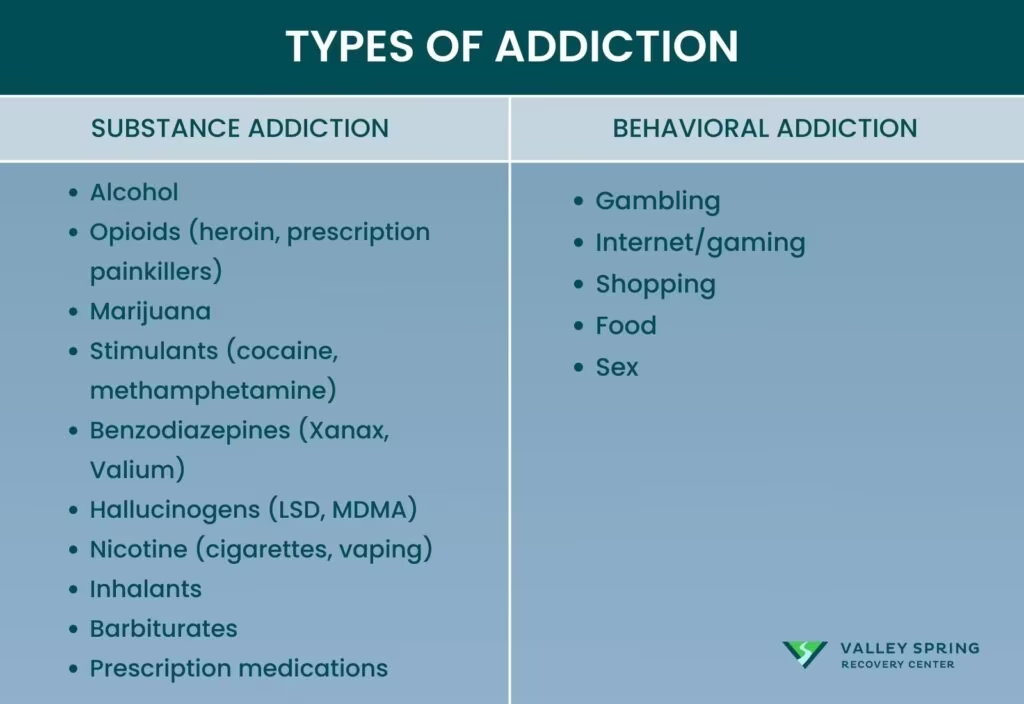
Substance addiction covers the alcohol and drug use disorders tracked by federal survey data. Alcohol is the most common substance used among people 12 and older in the United States, according to the CDC, and alcohol use disorder affected 27.9 million Americans in 2024.
Drug addiction — spanning opioids, stimulants, cannabis, sedatives, and hallucinogens — affected 28.2 million people, or 9.8 percent of Americans 12 or older, up from 8.7 percent in 2021, per the 2024 NSDUH.
Retail availability creates a separate classification problem because products sold beside snacks or supplements do not belong to one pharmacological class. The gas station drugs guide distinguishes tianeptine, kratom and concentrated 7-OH, synthetic cannabinoids, intoxicating hemp products, and nitrous oxide by active ingredient, effect, dependence risk, and legal status.
The following table compares the 4 largest substance classes by past-year use disorder prevalence and by FDA-approved medication availability, using figures from SAMHSA's 2024 NSDUH annual national report and medication lists published by SAMHSA and NIDA.
| Substance class | Example substances | Americans 12+ with a past-year use disorder (2024) | FDA-approved medications |
| Alcohol | Beer, wine, liquor | 27.9 million (9.7%) | Acamprosate, disulfiram, naltrexone |
| Marijuana (cannabis) | THC flower, edibles, concentrates | 20.6 million (7.1%) | None — treated with cognitive behavioral therapy, motivational enhancement therapy, and contingency management |
| Opioids | Heroin, fentanyl, oxycodone, hydrocodone | 4.8 million | Buprenorphine, methadone, naltrexone |
| CNS stimulants | Cocaine, methamphetamine, prescription stimulants | 4.3 million (1.5%) | None — contingency management is the best-studied treatment |
Behavioral addiction is compulsive engagement in a rewarding activity rather than use of a psychoactive substance. Gambling disorder holds full DSM-5 diagnostic status, while proposed behavioral addictions involving gaming, shopping, sex, exercise, food, and internet use require assessment of craving, impaired control, continued behavior despite harm, and competing diagnoses.
Across both types, the same risk factors decide who develops addiction and who does not.
What Causes Addiction?
Addiction is caused by the interaction of biological, environmental, and developmental risk factors — no single factor determines whether a person will become addicted to drugs, according to NIDA's report "Drug Misuse and Addiction." NIDA estimates that genes, including the effects environmental factors have on gene expression, account for 40 to 60 percent of risk; the evidence on genetics and addiction vulnerability separates inherited susceptibility from deterministic claims.
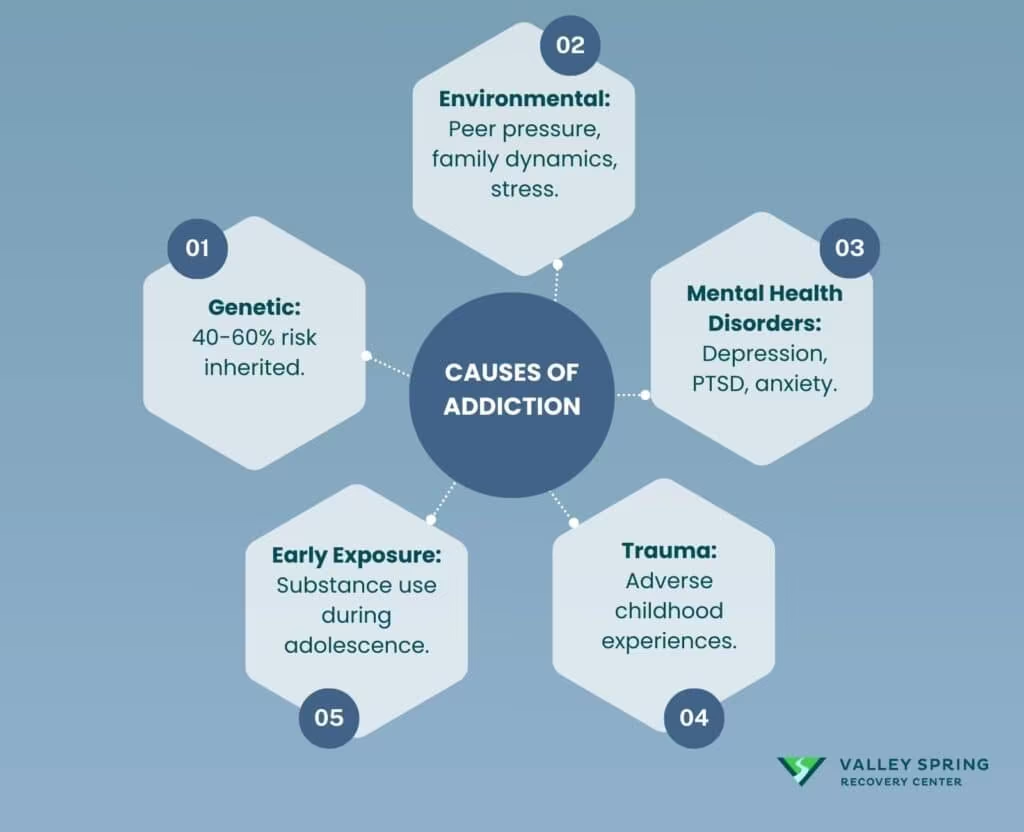
NIDA groups addiction risk factors into 3 domains:
- Biology: Genes, including the effects of environment on gene expression, account for 40 to 60 percent of addiction risk, and NIDA lists a person's stage of development among the biological factors that modify that baseline.
- Environment: Family, school, and neighborhood conditions shape exposure and coping. Parents or older family members who use drugs or misuse alcohol increase children's risk of future drug problems, per NIDA, and teens who use drugs sway other adolescents to try drugs for the first time.
- Development: The brain continues to develop into adulthood, and the prefrontal cortex — the region NIDA credits with assessing situations, making sound decisions, and keeping emotions and desires under control — is still forming during adolescence. The earlier people begin to use drugs, the more likely they are to develop serious problems, according to NIDA.
Risk factors predict vulnerability; the DSM-5 criteria identify when substance use has crossed into disorder.
What Are the Signs and Symptoms of Addiction?
The signs and symptoms of addiction are the 11 DSM-5 substance use disorder criteria, which the American Psychiatric Association groups into impaired control, social impairment, risky use, and pharmacological criteria (tolerance and withdrawal). A person meeting 2 or more criteria within 12 months qualifies for the diagnosis, per Jahan and Burgess's 2023 StatPearls review "Substance Use Disorder."
The 11 criteria fall into 4 clusters:
- Impaired control: taking the substance in larger amounts or for longer than intended, repeated unsuccessful attempts to cut down, excessive time spent obtaining or recovering from the substance, and craving.
- Social impairment: failing obligations at work, school, or home; continuing use despite relationship damage; and abandoning occupational, social, or recreational activities.
- Risky use: using the substance in physically hazardous situations, and continuing use despite a physical or psychological problem the substance causes or worsens.
- Pharmacological adaptation: tolerance, in which the same dose produces less effect, and withdrawal, in which stopping produces physical and psychological symptoms.
Criterion count sets severity: 2 to 3 criteria is a mild disorder, 4 to 5 is moderate, and 6 or more is severe. Among the 4.8 million Americans with a past-year opioid use disorder in 2024, 65.4 percent had a mild disorder and 19.3 percent had a severe disorder, per the 2024 NSDUH annual national report. Untreated, those symptoms compound into measurable physical, psychological, and social damage.
What Are the Effects of Addiction?
The effects of addiction are premature death, chronic physical disease, mental health deterioration, and progressive damage to relationships, work, and finances. The physical effects of drug use vary by substance class, dose, route, and duration. Overdose is the sharpest effect: the United States recorded 79,384 drug overdose deaths in 2024, according to Garnett, Matthew F. and Miniño, Arialdi M.'s January 2026 report "Drug Overdose Deaths in the United States, 2023-2024," National Center for Health Statistics.
The 2024 total marks a turning point. The age-adjusted overdose death rate fell from 31.3 to 23.1 deaths per 100,000 — a 26.2 percent decline, the largest one-year drop of the 2014-2024 period — and the death rate involving synthetic opioids other than methadone, the category dominated by fentanyl, fell 35.6 percent. The full breakdown by age, sex, race, and drug type appears in the CDC's NCHS Data Brief No. 549.
Alcohol kills on a longer clock. Excessive alcohol use caused about 178,000 U.S. deaths each year during 2020-2021 and shortened the lives of those who died by an average of 24 years, according to the CDC's "Facts About U.S. Deaths from Excessive Alcohol Use." Two-thirds of those deaths — about 117,000 per year — came from chronic conditions, including liver disease, heart disease, and cancer.
New Jersey mirrors the national decline. The state recorded more than 2,800 overdose deaths in 2023 — more than 7 residents per day — an 11 percent decline from 2022, with preliminary 2024 data showing a further decrease, according to the New Jersey Department of Health's August 2025 announcement. The state operated 54 authorized harm reduction centers as of July 31, 2025, with at least one in each of New Jersey's 21 counties.
Mortality statistics understate the damage, because addiction affects relationships through lost trust, disrupted parenting, social isolation, conflict, and employment instability. Measuring the damage in a single person starts with formal diagnosis.
How Is Addiction Diagnosed?
Addiction is diagnosed through a clinical interview that scores the 11 DSM-5 substance use disorder criteria, supported by validated screening instruments including the AUDIT (Alcohol Use Disorders Identification Test), the DAST-10 (Drug Abuse Screening Test), and the CAGE questionnaire.
Screening precedes diagnosis. Standardized instruments flag a probable disorder in minutes; the library of drug addiction screening tests explains 15 instruments, their scoring thresholds, and the settings where each applies. A positive screen leads to a diagnostic evaluation with a clinician, and the evaluation feeds placement: the ASAM Criteria — the American Society of Addiction Medicine's placement framework — match a patient's diagnosis severity, withdrawal risk, and recovery environment to a numbered level of care.
A substance-use screen does not diagnose depression, anxiety, trauma, psychosis, or another psychiatric condition. Persistent psychiatric symptoms require a separate clinical evaluation, while mental health screening instruments identify which symptom domains need deeper assessment.
Placement matters because addiction treatment is a sequence of matched levels, not a single event.
What Are the Treatments for Addiction?
The treatments for addiction are behavioral therapy, FDA-approved medication, and structured levels of care matched to disorder severity. The combination of medication and counseling successfully treats substance use disorders and improves patient survival rates, according to SAMHSA's guidance "Treatment Options for Substance Use Disorder."

Medication is the evidence anchor for two disorders. The FDA has approved acamprosate, disulfiram, and naltrexone for alcohol use disorder, and buprenorphine, methadone, and naltrexone for opioid use disorder, per SAMHSA. People with opioid use disorder who are treated with methadone or buprenorphine are less likely to die or to have an overdose than those who do not receive treatment, according to NIDA's research report "Medications to Treat Opioid Use Disorder." Uptake stays low: 17.0 percent of Americans with a past-year opioid use disorder received medications for it in 2024, and 2.5 percent of those with alcohol use disorder received medications for that disorder, per the 2024 NSDUH.
Behavioral therapy carries the substance classes that lack an approved medication. Contingency management — a structured incentive program — is the best-studied treatment for methamphetamine use disorder and the one most associated with treatment success, according to NIDA. Drug addiction treatment combines substance-specific medications where approved, behavioral therapies, an appropriate level of care, and continuing recovery support.
How Does Valley Spring Treat Addiction in New Jersey?
Valley Spring treats substance use disorders through Partial Care, Intensive Outpatient, and Outpatient services under New Jersey substance use treatment license #200887. These ASAM-numbered levels reduce in intensity as clinical stability, daily functioning, and recovery support increase.
The following table compares the schedule and expected duration of each level at the Norwood, Bergen County facility. Partial Care is the New Jersey licensure term for what national frameworks call a partial hospitalization program (PHP); it is day treatment, and clients live at home.
| Stage | Level of care | ASAM level | Schedule | Duration |
| Restore | Partial Care (PHP) | 2.5 | 9 AM-3 PM Monday-Friday, plus 9 AM-12 PM Saturday | 4 to 6 weeks |
| Activate | Intensive Outpatient (IOP) | 2.1 | 6-9 PM, Monday-Friday | 6 to 8 weeks |
| Accelerate | Outpatient (OP) | 1.5 | 1-2 nights per week | 8 to 12 weeks, then ongoing as clinically needed |
Valley Spring caps its therapist-to-patient ratio at 8:1 and runs process caseloads of eight clients per therapist. On-site medication treatment uses buprenorphine (Suboxone and Brixadi) and naltrexone (Vivitrol), while individual therapy, group counseling, and family support address behavior, relationships, and relapse risk.
Treatment starts recovery; maintaining recovery is its own clinical phase.
How Do People Recover From Addiction?
People recover from addiction at rates comparable to other chronic illnesses, through sustained treatment, relapse management, and long-term support. In 2024, 74.3 percent of the 31.7 million U.S. adults who perceived they ever had a problem with alcohol or drugs — 23.5 million people — considered themselves to be in recovery or to have recovered, according to SAMHSA's 2024 NSDUH.
Relapse rates for substance use disorders run 40 to 60 percent, comparable to relapse rates for hypertension and asthma at 50 to 70 percent, according to NIDA's report "Treatment and Recovery." A return to use signals that treatment needs to resume or adjust, the same way a blood pressure spike signals a medication change — not a moral failure. Recovery from addiction includes monitoring warning signs, using a relapse-prevention plan, and maintaining long-term support.
Help is available at 3 levels of urgency. Call or text 988, or chat at 988lifeline.org, to reach the 988 Suicide and Crisis Lifeline for any mental health or substance use crisis. Call SAMHSA's National Helpline at 1-800-662-4357 for 24/7 treatment referrals nationwide. Call Valley Spring Recovery Center at (201) 781-8812 to speak with the Norwood, New Jersey admissions team about a clinical assessment and insurance verification.
What Are the Most Common Questions About Addiction?
The questions below explain how addiction is identified, how physical dependence differs from addiction, when withdrawal becomes urgent, and how treatment and recovery work.
Is Addiction a Disease?
Yes. NIDA defines addiction as a chronic, relapsing disorder and a brain disorder because repeated substance use changes circuits involved in reward, stress, and self-control. Addiction changes the brain through dopamine signaling, neuroplasticity, craving, and impaired control.
How Is Substance Use Disorder Diagnosed?
A clinician diagnoses substance use disorder when at least 2 of the DSM-5's 11 criteria occur within 12 months. The criteria measure impaired control, social impairment, risky use, tolerance, and withdrawal; 2 to 3 indicate mild severity, 4 to 5 moderate severity, and 6 or more severe severity. Addiction assessment and early detection begin with screening, while diagnosis requires a clinician to evaluate the full criteria and competing explanations.
What Is the Difference Between Drug Dependence and Addiction?
Physical dependence means the body has adapted to a substance and develops withdrawal when exposure stops; addiction adds compulsive use despite harm and impaired control. Dependence occurs with prescribed medication used correctly and does not by itself establish addiction. The comparison of drug misuse, dependence, and addiction separates these related clinical concepts.
When Does Drug or Alcohol Withdrawal Require Medical Care?
Withdrawal requires urgent medical assessment when it causes seizures, hallucinations, severe confusion, chest pain, breathing difficulty, persistent vomiting, loss of consciousness, or rapidly worsening symptoms. Alcohol and benzodiazepine withdrawal carry risks of life-threatening seizures or delirium, while opioid withdrawal creates serious dehydration and return-to-use risk. Drug withdrawal timelines, warning signs, and medical risks differ by substance.
How Long Does Addiction Treatment Take?
Treatment duration depends on withdrawal risk, disorder severity, physical and mental health, recovery environment, and response to care. How long drug rehabilitation lasts therefore differs across detox, residential, Partial Care, intensive outpatient, outpatient, and continuing-care settings.
Which Treatments Work for Substance Use Disorders?
Effective treatment combines behavioral therapy, medication when one is approved for the disorder, treatment of co-occurring health conditions, and support matched to the person's clinical needs. The overview of drug addiction treatment compares medications, therapies, levels of care, and continuing support without treating one method as appropriate for every substance.
Is Relapse Part of Addiction Recovery?
A return to substance use occurs in many chronic recovery courses, but it is not inevitable and does not mean treatment failed. It signals a need to reassess triggers, medication, support, or treatment intensity. Recognizing the warning signs of relapse creates an opportunity to intervene before substance use resumes.
Are Behavioral Addictions Real Diagnoses?
Yes, but not every repetitive behavior is a recognized addictive disorder. The DSM-5 moved gambling disorder into the substance-related and addictive disorders chapter, while other proposed behavioral addictions require careful evaluation for impaired control, functional harm, and competing diagnoses.
Can Addiction Be Cured?
Addiction is treated and managed rather than described as cured. Evidence-based care helps people stop substance use, restore health and functioning, and sustain recovery; recurrence calls for a treatment adjustment rather than moral judgment. Recovery from addiction depends on maintenance planning, relapse-prevention skills, social support, and long-term health care.
Sources & References17ShowHide
- SAMHSA — SAMHSA Releases Annual National Survey on Drug Use and Health (July 28, 2025) — 48.4 million / 16.8% with a past-year SUD; 27.9M alcohol use disorder; drug use disorder 9.8% (up from 8.7% in 2021); 4.8M opioid use disorder; 19.3% / 10.2M received needed treatment; 17.0% / 818,000 received MOUD; 2.5% / 697,000 received MAUD; 74.3% / 23.5M of 31.7M adults in recovery; 988 call, text, and chat channels.
- SAMHSA — Key Substance Use and Mental Health Indicators in the United States: Results from the 2024 NSDUH (annual national report) — Marijuana use disorder 20.6 million / 7.1%; CNS stimulant use disorder 4.3 million / 1.5%; drug use disorder 28.2 million / 9.8%; alcohol use disorder 27.9 million / 9.7%; OUD severity split (65.4% mild, 19.3% severe); DSM-5 2-or-more-criteria threshold used by NSDUH.
- CDC NCHS — Garnett MF, Miniño AM. Drug Overdose Deaths in the United States, 2023-2024. NCHS Data Brief No. 549, January 2026 — 79,384 U.S. drug overdose deaths in 2024; age-adjusted rate fell 26.2% (31.3 to 23.1 per 100,000), largest one-year drop of 2014-2024; synthetic opioids other than methadone rate fell 35.6% (22.2 to 14.3); National Vital Statistics System data.
- New Jersey Department of Health — New Jersey Marks Progress in Reducing Overdose Deaths While Honoring Lives Lost (August 29, 2025) — More than 2,800 NJ overdose deaths in 2023 (more than seven residents per day), an 11% decline from 2022; preliminary 2024 data shows a further decrease; 54 authorized harm reduction centers as of July 31, 2025, at least one in each of NJ's 21 counties.
- NIDA — Drug Misuse and Addiction (Drugs, Brains, and Behavior: The Science of Addiction) — Definition of addiction as a chronic, relapsing disorder and brain disorder (reward, stress, self-control circuits); genes plus epigenetics account for 40-60% of addiction risk; no single factor determines addiction; biology/environment/development risk domains; earlier drug use raises the chance of serious problems; lower striatal D2 dopamine receptor levels in people with a history of cocaine use disorder.
- NIDA — Treatment and Recovery (Drugs, Brains, and Behavior: The Science of Addiction) — Relapse rates for substance use disorders 40-60%, comparable to hypertension and asthma (50-70%); addiction is a treatable disorder; treatment enables people to counteract addiction's disruptive effects; medication as first-line treatment for opioid addiction combined with behavioral therapy.
- NIDA — Principles of Drug Addiction Treatment: A Research-Based Guide, Third Edition — Treatment duration, the evidence supporting adequate time in treatment, continuing care, and the need to match services to each person's changing clinical needs.
- SAMHSA — TIP 45: Detoxification and Substance Abuse Treatment — Withdrawal-management assessment, acute stabilization, substance-specific risk, and transition from detoxification into continuing treatment.
- FDA — Boxed Warning Updated to Improve Safe Use of Benzodiazepine Drug Class (2020) — Physical dependence and the risk of life-threatening withdrawal reactions, including seizures, when benzodiazepines are stopped abruptly or reduced too quickly.
- NIDA — Efficacy of Medications to Treat Opioid Use Disorder — People with opioid use disorder treated with methadone or buprenorphine are less likely to die or to have an overdose than those who do not receive treatment.
- SAMHSA — Treatment Options for Substance Use Disorder — FDA-approved medications: acamprosate, disulfiram, naltrexone for alcohol use disorder; buprenorphine, methadone, naltrexone for opioid use disorder; medication plus counseling successfully treats SUDs and improves patient survival rates.
- CDC — Facts About U.S. Deaths from Excessive Alcohol Use — About 178,000 U.S. deaths per year from excessive alcohol use (2020-2021); lives shortened by an average of 24 years; about two-thirds (117,000/year) from chronic conditions; alcohol is the most common substance used among people 12 and older.
- NIDA — What treatments are effective for people who misuse methamphetamine? — No FDA-approved medication for methamphetamine use disorder or any other stimulant use disorder; contingency management is the best-studied treatment and the one most associated with treatment success.
- NIDA — Cannabis (Marijuana) research topic — No FDA-approved medications for cannabis use disorder; behavioral treatments used are cognitive behavioral therapy, motivational enhancement therapy, and contingency management.
- American Psychiatric Association — Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR), Substance-Related and Addictive Disorders chapter — The 11 substance use disorder criteria and their grouping into impaired control, social impairment, risky use, and pharmacological criteria. Print reference — psychiatry.org blocks automated verification, so no URL is asserted.
- StatPearls (NCBI Bookshelf) — Jahan AR, Burgess DM. Substance Use Disorder (updated 2023) — DSM-5 diagnoses SUD against 11 criteria; severity thresholds 2-3 mild, 4-5 moderate, 6+ severe; tolerance criterion omitted for medications used under physician supervision.
- Rash CJ, Petry NM. Gambling Disorder in the DSM-5. Current Addiction Reports, 2016 (PMC) — DSM-5 moved gambling disorder from the Impulse Control Disorders chapter into the expanded Substance-Related and Addictive Disorders section — formal recognition of behavioral addiction.